


Layer 1 — Video & Communication Infrastructure
WebRTC (Twilio, Agora, Daily.co) at $0.004–0.01/minute, or a BAA-backed healthcare SDK.









Each layer needs distinct decisions — one wrong call cascades.
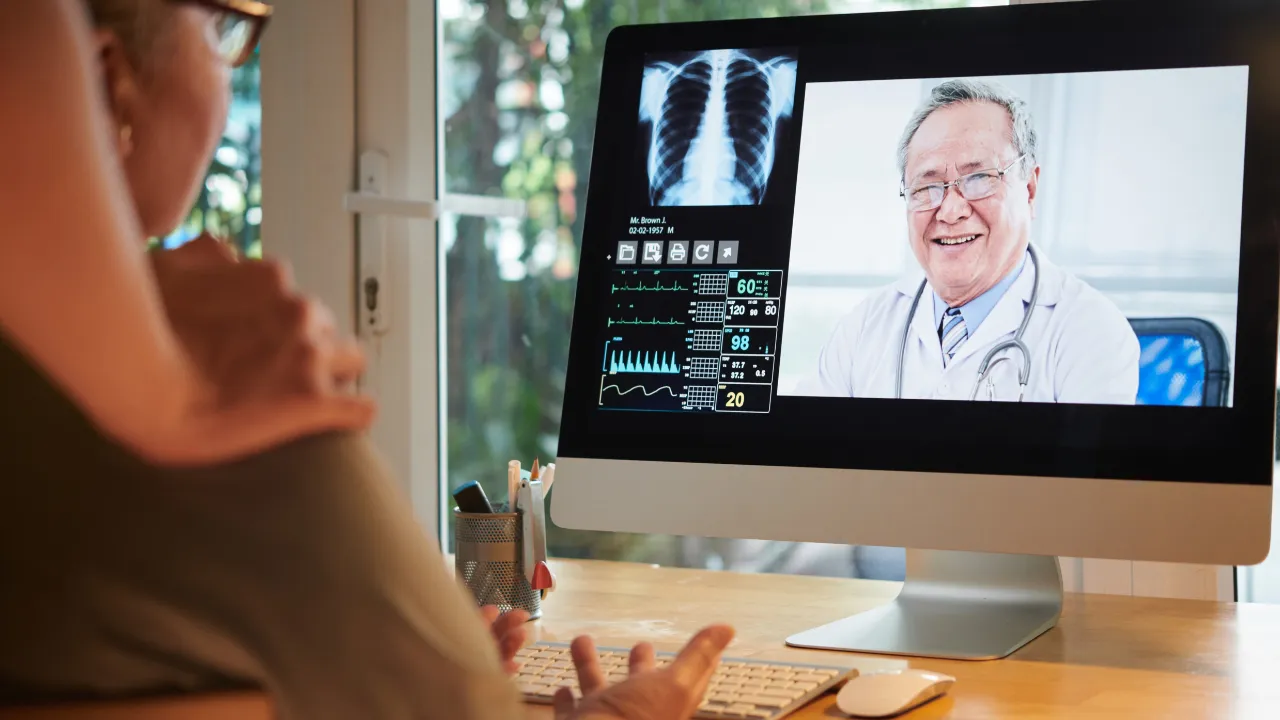
WebRTC (Twilio, Agora, Daily.co) at $0.004–0.01/minute, or a BAA-backed healthcare SDK.
Extend the EHR scheduler (Epic, Oracle Health), or build custom logic in 4–12 weeks.
Identity APIs (Jumio, Persona, Onfido) cost $1–5; multi-state licensure adds complexity.
Epic and Oracle Health run native telehealth; ambient scribes cost $200–500 per provider.
Stripe or Braintree at ~2.9% + $0.30; insurance billing needs RCM (Waystar, Availity).
Decide before architecture is locked.


Four places in the telemedicine stack where AI delivers measurable operational impact.
Notes draft in real time so providers recover post-shift charting hours at $200–500/provider/month.
Triage intelligence reads incoming messages, assesses urgency, and flags what needs immediate attention.
Forecasting models on scheduling history help operations anticipate capacity before wait times climb.
History at encounter start, drug-interaction checks, and protocol reminders keep telehealth on par with in-person.
The decisions teams get wrong most often — each one creating rework that is expensive to fix later.
Adaptive bitrate, audio-only fallback, and auto-reconnect are not optional.
Scheduling in isolation keeps telemedicine visits out of the clinical record.
Licensure tracking must exist before the provider network expands.
Retrofitting HIPAA before an enterprise sale is the costliest rework.
Telehealth coding keeps changing — scope RCM as its own workstream.
Infrastructure costs and development investment by stage — early MVP through enterprise scale. If you need the platform built, see our telemedicine app development company page for how we scope and deliver it.
Talk About Virtual CareFederal and state rules, still evolving.

Medicare flexibilities extended through end-2026.

Practice, prescribing, and consent rules vary by state.

DEA rules govern controlled substances via telehealth.

IMLC eases multi-state licensure, not license tracking.
Every platform handling PHI is a HIPAA Business Associate.
Scope these during architecture, not after.
PHI encryption, access controls, audit logs, and BAAs.
Third-party audited controls across the full stack.
Federal and state prescribing rules — EPCS and PDMP.
Telehealth codes and modifiers differ from in-person.
Standards that connect the encounter to the record.
Clinical decision support may meet FDA SaMD rules.
Every kind of healthcare organization.
Telemedicine platforms that hold up in production start with the care delivery model — patients, encounter types, provider workflow — not the technology. Our healthcare engineers guide you from video infrastructure to multi-state compliance to EHR integration.
Book a Free Consultation
100 Fastest Growth Companies
Global Spring Winner
Top App Development Company
AWS Partner Network
Google Cloud Partner
Highly Rated on Trustpilot
Verified Agency
Top App Development Company
ASSOCHAM Member
Our working estimates by stage: an early-stage MVP (under 500 monthly visits) with video, scheduling and basic EHR integration typically costs $150K to $400K to build, with infrastructure around $500 to $2,000 a month. Growth-stage platforms (5K to 20K visits) run about $8K to $25K a month in infrastructure, and enterprise scale (50K+ visits) $50K to $200K+ a month. Integrations, identity verification and ambient documentation move the number most.
Underinvesting in video reliability, scheduling outside the EHR, and late HIPAA work.
Medicare flexibilities run through end-2026; state practice rules still vary widely.


